American Top Team Aventura/NMB is registered with the State of Florida as a Health Studio. Registration No. is HS150100.
1. CHILD’S INFORMATION
Child's Name: _______________________ Date of Birth: ______________ Age: _______ Male / Female
Grade in September 20__: _______________________________ School Name: ____________________
2nd Child's Name: _______________________ Date of Birth: ______________ Age: _______ Male / Female
Grade in September 20__: _______________________________ School Name: ____________________
Child's Interest: ____________________________________
2. PARENT/GUARDIAN INFORMATION
Mother's Name: ___________________________ Cell#: __________________ Email: ____________________________
Father's Name: ___________________________ Cell#: __________________ Email: ____________________________
Address: _____________________________________ City: _________________ Zip: _____________
Referred By: _____________________________________________
3. PICK-UP AUTHORIZATION / EMERGENCY CONTACT INFORMATION
The following is a list of people who are authorized to pick up my child(ren) from American Top Team Camp. I will notify the
camp of any pick-up changes for the day (if applicable). Proper identification will be required for anyone picking up your
child(ren).
In the event of an emergency, American Top Team will attempt to contact a Parent/Guardian. Please provide two additional
people who have authority to make all decisions regarding your child(ren) if we are unable to reach a Parent/Guardian.
Name: _________________________ Phone: ____________________ Relationship: ______________________
Name: _________________________ Phone: ____________________ Relationship: ______________________
4. MEDICAL CONTACT INFORMATION
Does your child have allergies/medical condition? ■ No ■ Yes
If "yes," please indicate the type of allergy: __________________________________________________
5. FEE AGREEMENT — CHARGES FOR HEALTH STUDIO SERVICES
My initial below certifies I understand:
_____ I am obligated to update all payment information as needed.
_____ All billing is done by credit card authorization. The set amount will be withdrawn from my account bi-weekly.
_____ All returned payments are subject to a $5 processing fee and payments rejected for insufficient funds or a closed
account may also be assessed a $35 NSF fee.
_____ In the event I default on my payments, my child(ren) will be released from the program and that I will be responsible for
any cost of collection, including attorney's fees.
_____ American Top Team does not issue Tax Statements, so all parents must keep track of information if it is needed. There
will be a $25 bookkeeping fee to print out all individual receipts.
_____ If my child(ren) are dropped off early or picked up late for the classes there will be an early/late fee of $15 after each
10-minute interval. This fee is per child, will continue accumulating until the child(ren) is/are picked up, and will be automatically
charged to my CC on file within one week of the infraction.
6. ATTENDANCE / WITHDRAWAL POLICY & CONTRACT TERM
_____ I understand that I must notify the Class Department within two weeks IN WRITING if I wish to withdraw my child from
classes, by sending an email to attaventuranmb@gmail.com.
_____ I understand that there are no refunds for absences due to sickness, vacations, mishaps, holidays, or unforeseen
circumstances. Make-up classes can be made up to the last day of the current period. Needs to be notified IN WRITING 24
hours in advance for child(ren) to be permitted with a valid excuse. Make-ups are based on availability and need to be made with
a similar age and level group.
_____ I understand that I am financially responsible for each bi-weekly tuition if I do not notify the Class Department of any
changes. I understand the center is honoring my child's spot in the class until told otherwise, in writing.
Contract Term (F.S. 501.017(7)): The initial contract term will not exceed thirty-six (36) months. Thereafter, this contract is
renewable only on an annual basis. Renewal contracts and the renewal fee may not be executed or collected until sixty (60)
days or less before the preceding contract term expires.
7. FACILITY ENTRY IDENTIFICATION
If American Top Team requires a member to furnish identification upon entry to the facility as a condition of using the health
studio's services, American Top Team will provide the member with the means of such identification (e.g., membership card, key
fob, or check-in credential).
8. CREDIT CARD INFORMATION *MANDATORY FOR ALL STUDENTS*
American Top Team does not issue refunds outside of the statutory rights described on the following page, but in some cases a
credit may be given at Management's discretion.
Payment amount: _______________________________ Description: ___________________________________________
Payment billed Bi-weekly
Credit Card Type: ■ Visa ■ MasterCard ■ Amex
Credit Card Number: _________________________________________ Exp. Date (MM/YY): ____ / ____
Name on Credit Card: _____________________________________________________________________________
A $15.00 declined transaction fee will be assessed for every declined transaction processed.
SIGN HERE ONLY FOR AUTOMATIC PAYMENT — Please charge Bi-Weekly tuition payment to my credit card.
Signature Parent/Guardian: _______________________________________________ Date: ____ / ____ / ______
By signing this agreement, the Parent/Guardian acknowledges having read, understood, and agreeing with all the terms and
conditions of this Agreement, including the Right-to-Cancel disclosures on the following page, which are placed in immediate
proximity to the signature line required below.
A SIGNED WAIVER IS REQUIRED FOR EVERY PARTICIPANT AND MUST BE SIGNED BY A PARENT/LEGAL GUARDIAN
FOR PARTICIPANTS UNDER 18 YEARS OF AGE. WAIVERS CAN BE COMPLETED ONLINE.
American Top Team Aventura/NMB
305-454-0686 · 2148 NE 164th St, NMB, FL 33162 · www.attaventuranmb.com
After School Program
REQUIRED RIGHT-TO-CANCEL DISCLOSURES — Sections 501.012–501.019, Florida Statutes
Read carefully before signing. These provisions are required by Florida law to appear in immediate proximity to the buyer's signature, in at
least 10-point boldfaced type.
1. Members are entitled to the penalty-free cancellation of this contract within 3 days, exclusive of holidays
and weekends, of its making, upon the mailing or delivery of written notice to American Top Team, and refund
upon such notice of all monies paid under the contract, except that American Top Team may retain an
amount computed by dividing the number of complete days in the contract term (or, if appropriate, the
number of occasions health studio services are to be rendered) into the total contract price and multiplying
the result by the number of complete days that have passed since the making of the contract or, if
appropriate, by the number of occasions that health studio services have been rendered. A refund shall be
issued within 30 days after receipt of the notice of cancellation.
2. Members are entitled to the cancellation and refund of the contract if the contracting business location of
American Top Team goes out of business, or moves its facilities more than five (5) driving miles and fails to
provide, within 30 days, a facility of equal quality located within five (5) driving miles at no additional cost to
the member.
3. A member's notice of intent to cancel shall be given in writing to American Top Team. Such notice of
cancellation shall also terminate automatically the member's obligation to any entity to whom American Top
Team has subrogated or assigned the member's contract. If American Top Team wishes to enforce such
contract after receipt of the notice, it may request the Department of Agriculture and Consumer Services to
determine the sufficiency of the notice.
4. If the Department determines that a refund is due the member, the refund shall be an amount computed by
dividing the contract price by the number of weeks in the contract term and multiplying the result by the
number of weeks remaining in the contract term. The business location of American Top Team shall not be
deemed out of business when temporarily closed for repair and renovation of the premises: (a) upon sale, for
not more than 14 consecutive days; or (b) during ownership, for not more than seven (7) consecutive days
and not more than two (2) periods of seven (7) consecutive days in any calendar year. A refund will be issued
within 30 days after receipt of the notice of cancellation.
5. Members are advised to contact the Florida Department of Agriculture & Consumer Services for
information within 60 days should American Top Team go out of business.
6. This contract may be cancelled if the member dies or becomes physically unable to avail themselves of a
substantial portion of the services used from the commencement of the contract until the time of disability,
with a refund computed by dividing the contract price by the number of weeks in the contract term and
multiplying the result by the number of weeks remaining in the contract term. The member or the member's
estate seeking relief under this paragraph may be required to provide proof of disability or death by
certification of a physician licensed under Chapter 458, 459, 460, or 461, Florida Statutes, to the extent the
diagnosis or treatment is within the physician's scope of practice. A refund shall be issued within 30 days
after receipt of the notice of cancellation.
7. The initial contract will not exceed thirty-six (36) months, and thereafter shall only be renewable annually.
Renewal contracts may not be executed and the renewal fee may not be paid until sixty (60) days or less
before the preceding contract expires.
8. If American Top Team requires a member to furnish identification upon entry to the facility as a condition of
using its services, American Top Team will provide the member with the means of such identification.
9. SHOULD YOU (THE BUYER) CHOOSE TO PAY FOR MORE THAN ONE (1) MONTH OF THIS AGREEMENT IN
ADVANCE, BE AWARE THAT YOU ARE PAYING FOR FUTURE SERVICES AND MAY BE RISKING LOSS OF
YOUR MONEY IN THE EVENT THIS HEALTH STUDIO AND/OR THIS BUSINESS LOCATION CEASES TO
OPERATE. THIS HEALTH STUDIO IS NOT REQUIRED BY FLORIDA LAW TO PROVIDE ANY SECURITY, AND
THERE MAY NOT BE OTHER PROTECTIONS PROVIDED TO YOU SHOULD YOU CHOOSE TO PAY IN
ADVANCE.
By signing below, I acknowledge that I have read and received the above Right-to-Cancel disclosures, which were provided to
me in immediate proximity to my signature as required by Section 501.017, Florida Statutes.
Signature of Participant's Parent or Guardian: _______________________________________ Date: ____ / ____ / ______
Signature of Staff Member: _______________________________________________ Date: ____ / ____ / ______
Disclaimer: This form incorporates the general provisions required by Sections 501.012–501.019, Florida Statutes, for health studio contracts,
based on the "Health Studio Contract Requirements Checklist" (Rev. 12/7/2020). It is provided for general informational purposes only and is
not a substitute for legal advice.
American Top Team Aventura/NMB
305-454-0686 · 2148 NE 164th St, NMB, FL 33162 · www.attaventuranmb.com
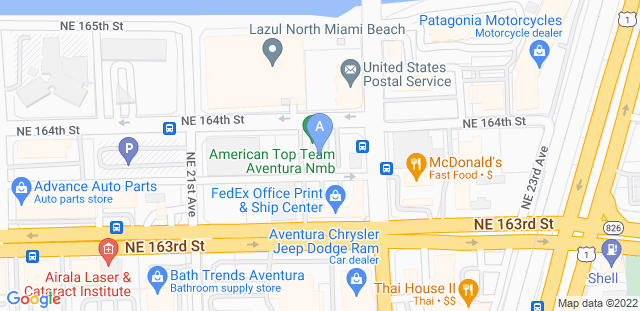
 American Top Team Aventura NMB